Strattera
Showing all 7 resultsSorted by popularity
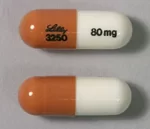
Generic Strattera 80 mg
In stock
Price range: $1,480.50 through $4,860.00
Generic Strattera 100 mg
In stock
Price range: $1,480.50 through $4,875.00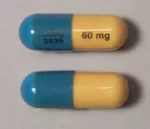
Generic Strattera 60 mg
In stock
Price range: $1,374.30 through $4,500.00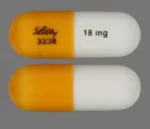
Generic Strattera 18 mg
In stock
Price range: $1,267.20 through $4,215.00
Generic Strattera 10 mg
In stock
Price range: $1,267.20 through $4,200.00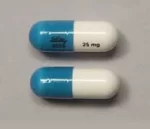
Generic Strattera 25 mg
In stock
Price range: $1,267.20 through $4,200.00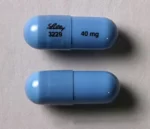
Generic Strattera 40 mg
In stock
Price range: $1,267.20 through $4,200.00In today’s time, both adults and children suffer from Attention deficit hyperactivity disorder. To deal with they are using various medications. Strattera is one of the most prescribed medicines for curing this disorder. An ADHD patient can buy Strattera online or at any nearby drug store.
It is a non-stimulant medication, making it a great choice for people who can’t tolerate stimulant drugs or have a history of substance abuse.
The working function of Strattera Drug:
Strattera contains generic Atomoxetine HCL, which is believed to assist via norepinephrine (a neurotransmitter in the brain) associated with attention, impulsivity, and hyperactivity.
It blocks norepinephrine reuptake that results in increased levels of the neurotransmitter in the brain, the action helps to relieve attention and behavioral abnormalities.
This medicine has another advantage which is its non-addictive nature unlike the stimulant medications allowing the risk of dependence to be reduced.
Uses of Strattera Medicine:
ADHD – Attention-Deficit/Hyperactivity Disorder is a neurodevelopmental abnormality like loss of attentiveness, forgetfulness, hyperactivity, emotional dysregulation, etc. This common disorder can be caused by various circumstances like stress, depression, smoking, excessive alcohol consumption, brain injury, etc. Strattera helps by increasing the levels of Norepinephrine (or noradrenaline) brain chemical, responsible for the transmission of nerve signals.
Apart from ADHD treatment, Strattera has also indicated potency in managing depression, anxiety, and some common types of learning disabilities.
Dose and Dosages:
Strattera oral capsules are available in adjustable dosage forms like 10mg,18mg,40mg,100mg and so on. The dosing strength must be increased or decreased upon the recommendation of the physician. It depends upon the patient’s age, their health condition and their response to the drug. After just a couple of weeks, one is able to feel its benefits.
Dosing for Children and Adolescents for ADHD – 0.5 mg/kg is the starting dose which can be further increases to 1.2 mg/kg after three days or longer considered administration via mouth. The maximum daily allowance that can be taken is 1. 4mg/kg (or 100 mg respectively) which must not be crossed.
In adults for ADHD treatment – The initial dose of 40 mg can be increased to 80 mg is used for oral administration after 3 days. In addition, After 2 to 4 weeks, the dose may be increased to a maximum of 100 mg.
Step-by-step introduction of Strattera into your treatment plan usually starts with a small dose under professional control that can be adjusted to reach best possible results. To understand Strattera, we should keep in mind that it may take some time up to several weeks to become fully effective. That’s why patience and consistency in the drug intake are essential.
Strattera Side Effects:
Nonetheless, like any medicine, it can cause some unpleasant side effects, such as nausea, dry mouth, drowsiness, and appetite changes which should be discussed with healthcare professionals constantly.
A few of its side effects are as follows-
- Fainting
- Seizures
- Confusion
- Shivering
- Dyspepsia
- Erectile dysfunction
- Hypoesthesia
- Somnolence
- Anorexia
- Abdominal pain
- Fatigue
- Paraesthesia
- Hyperhidrosis
- Dysuria
- Palpitations
- Rash
- Dizziness
- Libido decreased
- Sleep disorder
- Chills
Precautions:
- Do not mix Strattera with Alcohol and other seductive, it can create severe dizziness and withdrawal symptoms.
- In rare cases this drug can worsen the symptoms of ADHD including suicidal thoughts and unusual behavioral changes, which may require regular monitoring and immediate medical attention.
- To get the best suited dosage guide it is necessary to share the patient’s medical history and concurrently using drugs with the physician. It can help the doctor to adjust the dosage with low risk of unwanted effects.
- In several cases sudden death and stroke are reported, therefore it is classified as a prescription drug. Thus, one should take medical advice before using this drug.
- Do not take other stimulant drugs with Strattera to avoid any mishaps.
Why a Prescriber Might Choose Strattera Over a Stimulant
This is worth explaining directly, because the current page doesn’t address it at all, and it’s one of the most common questions patients and parents actually have. Strattera isn’t generally a first-line ADHD treatment. Stimulants (Adderall, Ritalin, Vyvanse, and others) tend to work faster and, for many patients, more effectively for core ADHD symptoms. But there are specific, recurring clinical reasons a prescriber reaches for Strattera instead:
Comorbid anxiety. Stimulants can sometimes worsen anxiety symptoms in people who have both ADHD and an anxiety disorder, a common overlap (see Anxiety vs. ADHD for how the two conditions can look similar or coexist). Atomoxetine doesn’t carry that same risk of aggravating anxiety, which makes it a common choice when anxiety is part of the clinical picture.
A personal or family history of substance misuse. Because Strattera has no meaningful abuse or diversion potential, it removes a variable that matters a great deal in households or individuals with a history of substance use disorder: there’s no street value, no risk of a child’s medication being misused by a sibling or peer, and no need for the refill-timing scrutiny that comes with a Schedule II stimulant.
Cardiac risk factors that complicate stimulant use. Atomoxetine still carries its own cardiovascular warning (above), so it isn’t a cardiac-risk-free alternative, but for some patients with borderline risk factors, a prescriber may judge the overall risk-benefit differently for a non-stimulant than for a Schedule II amphetamine or methylphenidate product. This is always an individualized decision, never a blanket rule.
24-hour coverage without a daily on/off pattern. Strattera is typically dosed once or twice daily and, once at a stable dose, provides steady round-the-clock coverage rather than the rise-and-fall pattern of a stimulant dose wearing off. For patients who found the “crash” as a stimulant wears off disruptive, this steadier profile is sometimes preferred, though it comes with a real tradeoff, covered next.
No diversion or misuse potential. Because it isn’t a controlled substance, there’s no risk of it being sought out, sold, or misused for performance or recreational effect the way stimulants sometimes are among students and young adults, a genuine, if less clinical, reason some patients and families prefer it.
None of this makes Strattera “safer” in some general sense: its boxed warning, liver-injury risk, and cardiovascular effects are real and serious. It means the type of risk is different, and the decision between a stimulant and Strattera is really a decision about which risk profile fits a specific patient, not a mildness ranking. If you’re weighing the two directly, Strattera vs. Adderall and Strattera vs. Vyvanse go through the practical differences in more depth, and Strattera vs. Wellbutrin covers how it compares against another non-stimulant option sometimes used off-label for ADHD.
Who Should Not Take Strattera
The FDA label’s formal Contraindications section for Strattera is short but specific, and worth understanding rather than just listing:
Strattera should not be used by anyone with a known hypersensitivity to atomoxetine or any ingredient in the capsule, which is the baseline contraindication on essentially every drug label.
It should not be started within 2 weeks of stopping a monoamine oxidase inhibitor (MAOI), and an MAOI should not be started until 2 weeks after stopping Strattera, because combining the two can affect brain monoamine levels in a way that’s genuinely dangerous, the same underlying concern as the MAOI contraindication on the stimulant labels in this project, even though the mechanism isn’t identical.
It’s contraindicated in narrow-angle glaucoma, because atomoxetine is associated with pupil dilation (mydriasis), which can worsen this specific type of glaucoma, a risk that doesn’t appear on the stimulant labels covered elsewhere in this project.
It’s contraindicated in anyone with pheochromocytoma, or a history of it: a rare adrenal-gland tumor that itself causes surges of the same stress hormones atomoxetine affects; combining the two can dangerously amplify blood pressure and heart rate.
And it’s contraindicated in severe cardiovascular disorders where the blood pressure and heart rate increases atomoxetine can cause would be expected to seriously worsen the underlying condition, a more absolute version of the cardiovascular caution already covered above.
As on the other drug pages in this project, it’s worth being explicit that contraindications and warnings-and-precautions are legally distinct sections of an FDA label: items that don’t appear on this specific list (like the liver and cardiovascular risks above) aren’t minor just because they’re filed differently; they’re simply warnings the FDA judged as needing case-by-case clinical judgment rather than an absolute bar. Give your prescriber a complete medical and family history, including cardiac, liver, and eye conditions, before starting.
The Liver Warning: What to Watch For
Severe liver injury from Strattera is rare, but it’s serious enough, and specific enough in its symptoms, that it’s worth a direct checklist rather than a general “tell your doctor about any side effects” line. Contact your prescriber the same day, not at the next scheduled visit, if you or your child notice:
- Yellowing of the skin or the whites of the eyes (jaundice)
- Dark urine
- Unexplained, persistent nausea
- Right-upper-abdominal pain or tenderness (the area under the right ribs, where the liver sits)
- Unexplained fatigue that doesn’t fit the usual pattern of medication side effects
- Itching without a rash
Post marketing reports include cases of liver failure, one of which required a liver transplant, though this remains rare relative to the overall number of patients who take Strattera without any liver problem. The FDA’s guidance is specific: if jaundice or lab evidence of liver injury shows up, Strattera should be stopped and should not be restarted, since re-exposure carries its own risk. This is a different kind of warning than the cardiovascular one above, because it depends on a patient or caregiver recognizing symptoms early, which is exactly why it’s listed as a checklist here rather than folded into a longer paragraph.
Heart, Blood Pressure, and a Less-Known Risk: Priapism
Atomoxetine’s cardiovascular effects are similar in kind to what’s covered on the stimulant pages in this project: modest average increases in blood pressure and heart rate, and the possibility of orthostatic symptoms (lightheadedness, occasional fainting on standing), but they’re worth restating here because the current page doesn’t mention them at all. Blood pressure and heart rate should be checked before starting and periodically during treatment, with extra caution in anyone with hypertension, a fast resting heart rate, or heart or blood vessel disease.
One risk is genuinely counterintuitive and worth calling out directly: priapism, a prolonged and often painful erection unrelated to sexual activity. It’s rare, but it’s on Strattera’s own FDA label, and a 2013 FDA drug safety communication specifically comparing ADHD medications found that priapism “appears to be more common in patients taking atomoxetine than in patients taking methylphenidate products,” meaning this isn’t a minor footnote borrowed from the stimulant warnings: it’s a risk that shows up more on this label than on Ritalin’s. Any erection lasting more than four hours, or one that’s painful, needs same-day emergency medical attention, not a message to a regular prescriber for the next available appointment.
This Is Not a Controlled Substance: What That Actually Means
Everything above should make clear that “non-stimulant” doesn’t mean “no real risk.” Strattera carries a boxed warning and serious rare risks of its own. But one thing genuinely is different, and it’s worth stating plainly since it doesn’t appear anywhere on the current page: Strattera is not a DEA-scheduled controlled substance.
In practical terms, that means: no federal abuse/dependence boxed warning like Adderall’s or Ritalin’s; no legal cap on refills tied to controlled-substance rules; no realistic street value or diversion risk, so no locked-cabinet requirement the way there is for a Schedule II stimulant in the household; and none of the counterfeit-pill risk this project’s Adderall page covers, which is specifically driven by Adderall’s DEA shortage history and street demand. There’s no comparable black-market demand for atomoxetine, so that entire risk category doesn’t apply here.
What doesn’t change: it’s still prescription-only, it still requires a valid prescription from a licensed prescriber, and the boxed warning, liver-injury risk, and cardiovascular effects covered above are exactly as real as they would be for a controlled substance. “Not controlled” describes its regulatory and misuse-potential status, not its overall safety profile.
What to Expect: The Slow-Onset Timeline
This is one of the most practically important things missing from the current page, because it’s the opposite of how stimulants work and catches people off guard: Strattera does not work right away.
There’s no single FDA-specified number of days, but clinical trials measuring Strattera’s efficacy tracked improvement over 6 to 10 weeks, and prescribers generally tell patients to expect a gradual build, not an immediate effect:
First 1–2 weeks: most patients notice little to no change in ADHD symptoms. This is expected, not a sign the medication isn’t working; unlike a stimulant, there’s no same-day effect to gauge against.
Weeks 2–4: some patients begin noticing subtle improvement, though this varies significantly person to person, and dose increases during this window (guided by a prescriber, not self-adjusted) are common as the medication is titrated toward an effective dose.
Weeks 6–10 and beyond: full therapeutic effect is typically assessed in this window. If there’s been little to no improvement by around 8 weeks at an adequate dose, that’s the point a prescriber typically reassesses rather than continuing to wait.
There’s also no comedown or “crash” to plan around the way there is with a stimulant wearing off each day, because Strattera doesn’t produce an acute effect in the first place, there’s nothing acute to wear off. That steadier profile is part of what some patients prefer about it (see above), but it means patience during the first several weeks is genuinely part of how this medication is meant to be used, not a sign of a problem.
Drug Interactions
Strattera’s interaction profile clusters around three distinct mechanisms, which is a more useful way to think about it than a flat list:
MAOI-related risk (do not combine). Strattera should not be taken with a monoamine oxidase inhibitor, or within 2 weeks of stopping one in either direction. This is a formal contraindication, not just a caution, because of the risk to brain monoamine levels described above.
CYP2D6 metabolism (needs dosing awareness). Atomoxetine is broken down primarily by the liver enzyme CYP2D6. Potent CYP2D6 inhibitors (paroxetine, fluoxetine, and quinidine are the ones specifically named on the label) can raise atomoxetine levels substantially, and dosage adjustment may be necessary when either is combined with Strattera. This matters even more for the roughly 7% of people who are naturally “poor metabolizers” through this pathway (more in Special Populations below), since they already process the drug more slowly on their own.
Cardiovascular potentiation (needs monitoring). Albuterol and other systemically-administered beta2-agonists can have their cardiovascular effects amplified when combined with Strattera, so this combination should be used with caution and closer monitoring rather than avoided outright, which is relevant for anyone on Strattera who also uses an asthma inhaler or nebulizer treatment with a systemic (not purely inhaled-local) effect.
This isn’t an exhaustive list. Bring your full medication list (prescription, over-the-counter, and supplements) to your prescriber or pharmacist before starting Strattera.
Missed a Dose?
Take it as soon as you remember, up to the total daily dose. Don’t take more than the prescribed amount in one day to make up for a missed dose. Because Strattera doesn’t have the same next-day rebound concerns as a stimulant, there’s no need to skip a late dose to protect sleep the way there is with the stimulant medications on this site; simply resume the normal schedule from the next dose onward if a full day is missed.
Special Populations
Children and adolescents. Height and weight should be tracked throughout treatment. Initial weight and height gain can lag for the first 9–12 months of treatment before rebounding. In longer trials, patients on average caught up to roughly 17.9 kg of weight gain and 19.4 cm of height gain over about 3 years, broadly in line with expected growth, though individual monitoring still matters. Strattera is FDA-approved starting at age 6; safety and effectiveness haven’t been established below that age.
Pregnancy. There are no adequate controlled studies in pregnant women; animal studies showed adverse developmental effects at certain dose levels. A pregnancy registry exists specifically to track outcomes in women exposed to ADHD medications, including Strattera (1-866-961-2388), a resource worth knowing about rather than an obligation, and enrollment is voluntary. As with the stimulant medications on this site, continuing or starting Strattera during pregnancy is a benefit-versus-risk conversation with a prescriber, not an automatic stop or continue.
Breastfeeding. It isn’t known whether atomoxetine passes into human breast milk (it does appear in animal milk). Given that uncertainty, this is worth discussing directly with a prescriber if you’re nursing rather than assuming either way.
Hepatic impairment. Because the liver clears atomoxetine, dosing needs to be reduced in anyone with impaired liver function; the label specifies initial and target doses reduced to 50% of normal in moderate impairment (Child-Pugh Class B) and to 25% of normal in severe impairment (Child-Pugh Class C). This is in addition to, not instead of, the liver-injury monitoring covered above.
CYP2D6 poor metabolizers. Roughly 7% of people have a genetic variation that makes them “poor metabolizers” through the CYP2D6 enzyme pathway atomoxetine relies on, meaning the drug clears more slowly and blood levels run higher at a given dose than in the general population. The label calls for a more conservative titration in this group: starting at a lower dose and only increasing after about 4 weeks if symptoms haven’t improved, rather than the faster titration used for typical metabolizers. Most patients don’t know their CYP2D6 status in advance; this is one reason dose increases are paced gradually and guided by response rather than assumed to be safe on a fixed schedule.
Older adults. Strattera’s clinical trials didn’t extensively study older adults, and the general cardiovascular cautions above apply with added weight in anyone more likely to have existing heart disease or hypertension.
Before You Start: Questions Worth Asking Your Prescriber
Because Strattera’s risk profile depends heavily on individual factors (liver function, cardiac history, CYP2D6 metabolism, age, and what else you’re taking), a short list of questions to bring to the conversation is more useful here than a generic FAQ:
- Given my (or my child’s) medical history, does anything above change how you’d dose or monitor this medication?
- How will we monitor for the liver and cardiovascular warnings above: baseline labs, blood pressure checks, or just symptom awareness?
- Realistically, how many weeks should we expect before judging whether this is working?
- If I’m already taking [a specific medication: antidepressant, asthma inhaler, blood pressure medication], does that change anything here?
- What specific symptoms should prompt a same-day call versus something to mention at the next visit?
Bringing a specific list like this tends to get more useful, individualized answers than a general “any questions?” at the end of an appointment, especially for a medication whose safety profile depends this much on individual factors rather than a one-size-fits-all warning.
Storage & Disposal
Storage: Keep Strattera in its original, labeled container, out of sight and reach of children and pets, at room temperature away from excess heat and moisture. Unlike the stimulant medications on this site, Strattera has no meaningful diversion or misuse value, so a locked cabinet isn’t a safety necessity for that reason, but it should still be kept out of reach of children, since an accidental ingestion, particularly by a young child, can still cause real harm.
Disposal: Atomoxetine is not on the FDA’s flush list. If a drug take-back location or DEA take-back event isn’t available, mix unused capsules with an unappealing substance like used coffee grounds or kitty litter, seal them in a bag or container, and place them in household trash, and scratch out personal information on the prescription label before discarding the bottle.